What the Anion Gap Shows in Blood Chemistry
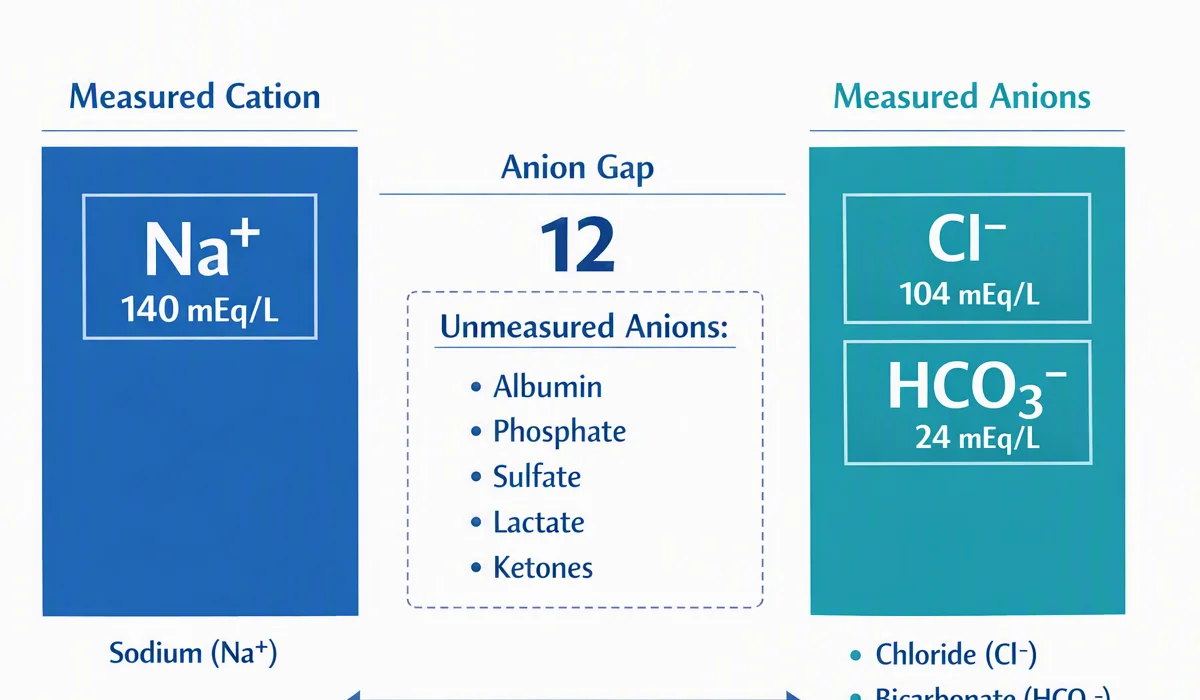
The anion gap is a derived value used in medical chemistry to aid in interpreting electrolytes and evaluate acid-base balance. It represents the difference between major measured cations and anions in the blood, mainly sodium and chloride, with bicarbonate included in the comparison. Because routine testing does not directly measure every ion in circulation, the anion gap can reveal the presence of unmeasured anions and other shifts in the body’s buffering system.
In practical lab interpretation, the anion gap is a supportive measure rather than a stand-alone diagnosis. It is often used to evaluate a possible acid-base disorder, especially when a clinician is trying to determine whether a metabolic disturbance is present. A normal result suggests the measured ions are balanced in a way that fits the expected electroneutrality of plasma, while an abnormal result can point to an electrolyte imbalance or hidden acids that are not obvious from the basic panel alone.
How an Anion Gap Calculator Operates
An Anion Gap Calculator employs a basic formula to the values provided from a lab report. Most calculators use serum sodium, serum chloride, and serum bicarbonate, and some also include potassium. The calculator then gives a calculated value that aids lab interpretation by indicating whether the measured ions suggest an acid-base issue.
In the standard approach, the calculator subtracts chloride and bicarbonate from sodium. If potassium is included, the formula may vary slightly, but the basic idea is the same: contrast major measured ions against the expected balance. Because the result is a calculated value, its meaning depends on the surrounding serum electrolytes, the patient’s clinical state, and the interpretive context of the rest of the report.
This makes the calculator useful as a diagnostic marker in clinical chemistry. It does not replace direct testing or clinical judgment, but it helps determine whether the lab result may reflect an anion deficit, anion excess, or a broader metabolic disturbance.
Standard Anion Gap Formula and Expected Range
The traditional anion gap formula is usually written as:
Anion gap = sodium − (chloride + bicarbonate)
Some laboratories also use a potassium-inclusive variation, but the sodium-based version is the most generally accepted in general lab science. The result is then compared with a normal range or reference interval supplied by the laboratory performing the test.
The specific reference interval can differ because different instruments, reagents, and reporting methods may produce slightly different values. That is why the result should always be interpreted against the lab’s own serum chemistry panel reference interval rather than relying on a universal cutoff. A result that appears abnormal in one lab may fall within another lab’s normal range.
From a lab science perspective, the anion gap is a helpful summary of the relationship between measured ions and unmeasured ions. It is not a direct measurement of acid or base, but rather a calculated clue that may indicate the need for additional testing, including a blood gas or additional chemistry studies.
Adjusted Anion Gap for Albumin
Albumin is a key unmeasured anion in blood, so low albumin can lower the apparent anion gap. This is why many clinicians and laboratorians evaluate a corrected anion gap when the patient has hypoalbuminemia. Without albumin correction, the result may diminish the presence of an acid load.
The corrected value is especially important in patients with illness, inflammation, malnutrition, liver disease, or fluid shifts that reduce albumin concentration. In these cases, the unadjusted anion gap may look normal even though a true acid-base problem exists. An albumin-adjusted interpretation helps reveal the hidden contribution of the reduced protein buffer.
For lab interpretation, albumin correction improves the utility of the anion gap as a diagnostic aid. It improves the connection between the numeric result and the patient’s real metabolic state. In other words, the corrected anion gap provides better interpretive context when low albumin could otherwise mask clinically important changes.
Elevated Anion Gap compared with Reduced Anion Gap
A elevated anion gap usually suggests excess acid or buildup of unmeasured anions. This pattern is often seen in metabolic acidosis, where bicarbonate is consumed as the body buffers acid. A high value is a indication that the balance between measured ions and unseen ions has shifted in a meaningful way.
A low anion gap is less common and can be due to lab or physiologic factors. It may indicate low albumin, abnormal proteins, or analytical issues, among other possibilities. Because the low result can be subtle, it is important to confirm the numbers and examine the broader electrolyte panel before reaching conclusions.
Both patterns require close lab interpretation. A high result often suggests added acids, while a low result may suggest reduced negative charge from albumin or measurement-related issues. Either way, the value should be read as part of the overall clinical picture rather than as an isolated finding.
Typical Causes of an Abnormal Anion Gap
A number of conditions can push the anion gap away from the expected value. One of the most important is lactic acidosis, in which lactate builds up as tissues generate energy under stress or inadequate oxygen availability. Another common cause is ketoacidosis, where ketone production increases and adds additional acids to the blood.
Renal failure can also cause an abnormal result because the kidneys are less able to eliminate acid and maintain normal electrolyte handling. As retained acids and related compounds increase, the gap may rise. In addition, toxins can cause a high anion gap by adding unusual acids or by interfering with metabolism in ways that https://anion-gap-calculation.com/causes/mudpile.html raise acid load.

These causes all fit the same general pattern: the body accumulates unmeasured ions or loses buffering capacity, and the calculated value increases. In the lab, this makes the anion gap a valuable clue in distinguishing one metabolic disturbance from another.
How to Use the Calculator Step by Step
Working with Anion Gap Calculator is straightforward when the lab values are available. Begin by locating the input values from the report, then enter the serum sodium, serum chloride, and serum bicarbonate. If the calculator allows it, include potassium as well.
Once you enter the numbers, review the calculated result and compare it with the lab’s reference range. When the tool provides a corrected output, enter the albumin value so the tool can estimate the corrected anion gap. This matters especially when hypoalbuminemia is present.
After the calculation is finished, interpret the result in context. A single number by itself does not identify an acid-base disorder by itself. Instead, use it as part of a wider assessment that includes the electrolyte panel, the serum chemistry panel, and any other available clinical information.
Patient & Laboratory Assessment Tips
Effective clinical interpretation begins with verifying whether the result matches the overall picture of acid base balance. Should the anion gap is high, look for signs of metabolic acidosis and consider whether the patient may have lactic acidosis, ketoacidosis, renal failure, or toxin exposure. If it the value is decreased, evaluate albumin, total protein, and the possibility of analytical variation.
A blood gas can be especially helpful because it gives direct information about pH, carbon dioxide, and bicarbonate handling. When paired with the anion gap, it gives a more complete view of whether there is a true acid-base disorder and whether compensation is occurring. This combination is often more useful than any one lab result alone.
It is also important to think about analytical pitfalls. Small shifts in measured ions can change the calculated value, and differences between instruments can affect the reported reference interval. For this reason, the anion gap should be interpreted alongside the electrolyte panel, the serum chemistry panel, and the patient’s clinical status. That approach improves diagnostic clarity and lowers the risk of overcalling or missing an abnormality.
Anion Gap Calculator FAQs
What is an anion gap calculator used for?
An Anion Gap Calculator is used to calculate the anion gap from lab values and help assess electrolyte balance, acid-base balance, and possible metabolic acidosis. It is a clinical aid that supports lab interpretation by highlighting changes in measured ions and unmeasured ions.
What is the normal anion gap range?
The normal range depends on the laboratory and its reference interval. Different methods and instruments can produce different expected values, so the result should always be compared with the range reported on the specific serum chemistry panel.
Why does low albumin affect the anion gap?
Albumin is a major unmeasured anion, so hypoalbuminemia can lower the measured anion gap. That is why an albumin correction or corrected anion gap is often needed to avoid missing an underlying acid-base disorder.
What causes a high anion gap?
A high anion gap is frequently seen with lactic acidosis, ketoacidosis, renal failure, and certain toxins. These issues raise unmeasured anions or limit the body’s ability to maintain acid-base balance.
Should the anion gap be read with other lab results?
Yes, it should. The anion gap should consistently be interpreted with the electrolyte panel, blood gas, albumin, and the rest of the clinical picture. This broader approach improves clinical interpretation and helps distinguish a true metabolic acidosis from other lab patterns.