What Is the Anion Gap and Why It Matters
The anion-gap value is a calculated value that assists clinicians assess acid-base balance by contrasting common blood electrolytes measured on routine blood testing. It is especially helpful when reviewing metabolic alkalosis or other forms of acid-base disturbance because it can show whether there are hidden acids or other shifts that are not obvious from the basic lab numbers alone.
In practical terms, the anion gap helps interpret the relationship between positively charged ions and negatively charged ions in the bloodstream. Most often, the main measured values are sodium, chloride, and bicarbonate, while other contributors such as albumin and hidden anions may influence the result. That is why the anion gap is more than a number; it is a clue that aids medical interpretation of a patient’s status.
Although the anion gap is commonly discussed in metabolic acidosis, it also matters in metabolic alkalosis because the surrounding clinical context https://anion-gap-calculation.com/faq/high-meaning.html can change how the result is read. A normal, corrected, or elevated value may suggest different underlying processes, especially when paired with other serum electrolytes and lab values from a chemistry panel.
In what way an Anion Gap Calculator Operates
An anion gap calculator is a medical calculator that handles the anion gap formula so you can easily review blood test results. The most common calculation formula is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
This equation uses serum sodium, serum chloride, and serum bicarbonate because they are the core values available on a standard electrolyte panel. Sodium is the principal measured cation, while chloride and bicarbonate are the principal measured anions used in the calculation. The result is then compared with a reference interval or reference range to determine whether the value is within range or unexpected.
Many calculators also offer an optional albumin adjustment. Since albumin is a important unmeasured anion, a low albumin level can make the anion gap appear deceptively normal. A carefully built calculator therefore acts as both a diagnostic tool and an interpretation guide, helping with clinical decision making when the numbers do not align with the expected pattern.
Anion Gap in Metabolic Alkalosis: Interpretation Basics
In alkalemia with metabolic cause, the body has a primary increase in bicarbonate or acid loss, and the anion gap may look unchanged, slightly changed, or elevated depending on the cause and the patient’s adaptive response. Understanding the anion gap in this setting requires more than simply reading the number; it requires attention to physiologic compensation and the full pattern of lab findings.
A standard anion gap in metabolic alkalosis often suggests that the alkalosis is due to loss of chloride, volume changes, or other processes that do not add excess acids to the bloodstream. An elevated result may suggest a combined disorder, such as concurrent metabolic acidosis, or hidden contributions from hidden anions. This is where albumin becomes important, because low albumin can mask a truly increased gap.
For that reason, many clinicians rely on the adjusted anion gap rather than the unadjusted value. The corrected value gives a more accurate picture of test interpretation, especially when metabolic alkalosis coexists with other changes in acid-base status. In short, the calculator does not replace judgment; it improves the quality of that judgment.
Required Inputs for the Calculator
A trustworthy calculator generally needs four inputs: serum sodium, serum chloride, serum bicarbonate, and serum albumin. These numbers are obtained from a standard blood chemistry panel or electrolyte panel, and each assists in refining the final interpretation.
- Serum sodium: the primary cation in the equation. Serum chloride: a significant measured anion that helps determine the gap. Serum bicarbonate: reflects buffering status and is central to acid-base assessment. Serum albumin: used in albumin correction when required.
These measurements also support wider lab result analysis. For instance, a low bicarbonate may suggest metabolic acidosis, while an elevated bicarbonate fits better with metabolic alkalosis. Chloride trends can help identify chloride-responsive patterns, and albumin helps prevent underestimating the anion gap in patients with hypoalbuminemia.
If any of these values are missing, interpretation becomes less precise. The calculator may still generate a number, but without the full dataset, the result may not reflect the true clinical context.
Step by Step Math Illustration
This is a basic calculation example using standard lab values:
- Sodium level: 140 Cl: 100 HCO3: 30
Applying the calculation:
Anion gap = 140 - (100 + 30) = 10

Provided that the applicable reference range is around 8 to 12, this result would be classified as a normal anion gap. With metabolic alkalosis in a patient, that may support a chloride driven or volume driven cause rather than a hidden acid load.
Now consider a different example:
- Sodium level: 140 Cl: 94 Bicarbonate level: 30
Anion gap = 140 - (94 + 30) = 16
This result may fit an elevated anion gap pattern depending on the lab’s reference interval. In a patient with metabolic alkalosis, that brings up the possibility of a mixed disorder or another process such as elevated lactate that is altering the overall interpretation.
Origins of alkalosis with Normal or Increased Anion Gap
A number of issues can cause alkalosis while the anion gap is left typical or turns unexpectedly high. The main practical reasons include vomiting, diuretic use, and volume depletion. These can lower chloride, affect renal processing of bicarbonate, and lead to a pattern that indicates alkalosis even when another issue is present.
Vomiting can result in loss of gastric acid, which elevates bicarbonate relative to chloride. Diuretic use often drives sodium and chloride loss, producing contraction alkalosis and a characteristic electrolyte pattern. Volume depletion can even more intensify renal bicarbonate retention and trigger a strong compensatory response.
An elevated gap in a patient who looks alkalotic should prompt careful review for overlapping disorders. One important example is lactic acidosis, which can coexist with alkalosis and raise the total gap. This is why the calculator should always be used as part of a larger clinical interpretation rather than as a standalone answer.
How to Correct the Anion Gap for Albumin
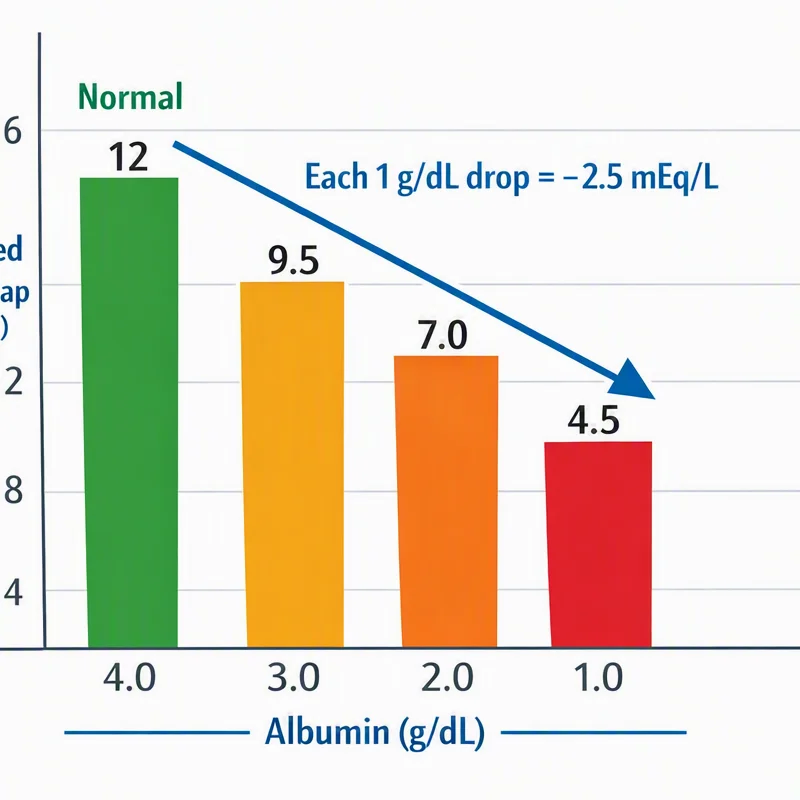
Albumin correction is essential because albumin is a negative protein that plays a major role to the unmeasured anion pool. When albumin is low, the measured anion gap may appear falsely normal. This is especially useful in patients with hypoalbuminemia, where the uncorrected number can miss the true acid burden.
Many clinicians use a corrected anion gap to improve lab interpretation. A common approach is to add a set amount for each gram per deciliter that albumin falls below normal, though the exact correction used can vary by institution. The key point is that a corrected anion gap gives a better picture of the patient’s acid-base status.
For example, a patient with a borderline-normal value may actually have an elevated corrected result after adjustment for albumin. That corrected value can change the overall reading from simple metabolic alkalosis to a mixed acid-base imbalance. This is why albumin should be reviewed together with serum sodium, serum chloride, and serum bicarbonate whenever possible.
When an Anion Gap Calculator Is Most Useful
An anion gap calculator is particularly helpful when a clinician wants quick, structured clinical decision support from a blood chemistry panel. It is especially helpful when the lab pattern is not immediately clear or when more than one process may be occurring at the same time.
Common situations include:
- Examining an electrolyte panel in a patient with unexplained bicarbonate changes Checking for hidden acid-base disorders in apparent metabolic alkalosis Comparing serial laboratory values during treatment Evaluating whether a corrected anion gap changes the interpretation Informing diagnosis when symptoms and labs do not match neatly
The tool is also helpful for documentation and communication. When the calculation is done in a consistent way, it provides a clear framework for discussing acid-base patterns with other clinicians. That consistency enhances clinical interpretation and helps avoid overlooking a mixed disorder.
Limitations and Common Calculation Errors
Even a well-designed calculator has constraints. Lab variability between instruments or facilities can shift the result slightly, and measurement error can affect sodium, chloride, or bicarbonate values enough to alter the final gap. Because the formula depends on small differences between numbers, even modest inconsistencies can matter.
Another major limitation is that the anion gap only reflects a portion of the body’s charged particles. It does not directly measure all acids or bases, and unmeasured anions may be present even when the value seems normal. That is why the result must always be considered in clinical context, not by itself.
Common calculation errors include entering the wrong units, using outdated values, or forgetting to apply albumin correction when indicated. Misreading the reference range is another common problem because different laboratories may use different reference intervals. A result that is normal in one setting may be slightly abnormal in another.
Finally, remember that an anion gap is never a substitute for a complete acid-base review. It is one part of the bigger picture that includes signs, prescriptions, volume status, and the broader pattern of serum electrolytes. When used correctly, it improves lab result analysis; used alone, it can be misleading.
FAQ About Anion Gap and Metabolic Alkalosis
What is an anion gap calculator used for?
An anion gap calculator is meant to efficiently determine the anion gap from serum sodium, serum chloride, and serum bicarbonate. It supports clinical interpretation of acid-base balance, reveals possible electrolyte imbalance, and aids evaluation of metabolic alkalosis or metabolic acidosis. When albumin is included, it can also deliver a corrected anion gap for better laboratory interpretation.
Can metabolic alkalosis affect the anion gap?
Yes. Metabolic alkalosis can be seen with a normal anion gap, and in some cases it may occur alongside an elevated anion gap if another disorder is present. The final reading depends on the clinical setting, albumin level, volume status, and whether there are unmeasured anions contributing to the result. This is why the anion gap calculator should be used as within a broader acid-base disorder assessment.
How do you calculate the anion gap from lab values?
The most common anion gap formula is serum sodium minus the sum of serum chloride and serum bicarbonate. That is, sodium - (chloride + bicarbonate). This calculation uses values from an electrolyte panel or blood chemistry panel and is then compared with the reference range to determine whether the result is normal or elevated.
Why should albumin be used to correct the anion gap?
Albumin should be used because it is a key unmeasured anion. When albumin is low, especially in hypoalbuminemia, the uncorrected anion gap may look falsely normal. Albumin correction helps reveal the corrected anion gap, which provides improved clinical interpretation and more accurate lab result analysis.
What is the meaning of a standard or elevated anion gap indicate in alkalosis?
A standard anion gap in metabolic alkalosis often indicates chloride loss, vomiting, diuretic use, or volume depletion. A high anion gap may indicate that another process may also be present, such as lactic acidosis or another acid-base disorder. The key is to read the value with the patient’s clinical context, albumin level, and full blood test results rather than using the number alone.